Marco Romanelli1, Alessandra Michelucci1, Massimiliano Minale2, Niccola Funel3*
1Dermatology Unit, University of Pisa, Italy
2Indipendent Researcher, Specialist in Pharmacology, Via R.De Blasio, 18 – 80034 Marigliano (Napoli); Italy
3Department of Laboratory Diagnostics and Transfusion Medicine, Clinical Chemical Analysis Laboratory, Pontedera Hospital - USL Tuscany North West, Pontedera, Italy
*Corresponding Author: Niccola Funel, Department of Laboratory Diagnostics and Transfusion Medicine, Clinical Chemical Analysis Laboratory, Pontedera Hospital - USL Tuscany North West, Via Roma, 147 - 56025 Pontedera, Italy
Received: 01 September 2026; Accepted: 04 September 2026; Published: 18 September 2026
Background: This interventional clinical study prospectively compared two hyaluronic acid (HA) fillers to combat nasolabial folds (NLFs). The main goal was to verify the effectiveness and safety of Foliage Intense (FI) over Belotero Intense (BI) by assessing the Wrinkle Severity Rating Scale (WSRS) score in aesthetic patients showing either moderate or severe NLF conditions.
Methods: Ninety-five patients were enrolled prospectively. To compare the two products, a double-randomized split-face model was used. The primary endpoints were the differences in the WSRS to demonstrate the efficacy of FI compared to BI after a six-month treatment (Wilcoxon rank test; p<0.05).
Results: In the Per Protocol (PP) analysis, the changes in the WSRS score from baseline to 6 months were -0.50±0.13 in the FI group and -0.48±0.12 in the BI group. Similarly, in the Intention to Treat (ITT) population, changes in WSRS scores from baseline to 6 months were -0.72±0.13 in the BI group and -0.73±0.14 in the FI group (p<0.001).
Conclusions: Overall, the mean score analyses revealed better results in FI applications compared to BI. However, the comparison did not show significant differences in terms of Global Aesthetic Improvement Scale (GAIS) or safety.
Nasolabial fold; Fillers; Wrinkle Severity Rating Scale; Global Aesthetic Improvement Scale; Hyaluronic acid; Prospective interventional study; Safety
Nasolabial fold articles; Fillers articles; Wrinkle Severity Rating Scale articles; Global Aesthetic Improvement Scale articles; Hyaluronic acid articles; Prospective interventional study articles; Safety articles
1. Introduction
1.1. State of the art
Nasolabial folds (NLFs), alternatively known as “laugh lines” [1,2], are caused by a va-riety of factors, including the loss of deep fat or muscle contour in the midface, a re-duction in hyaluronic acid content, and the degeneration of collagen and elastic fibers [3-5]. Over time, this leads to sagging of the skin and the formation of wrinkles and folds, widely known as skin aging. [6,7]. Skin aging is a natural process influenced by internal and external factors that, despite not being harmful, can affect quality of life in some individuals [8]. That is why minimally invasive aesthetic procedures, aiming to reverse the signs of aging, continue to progressively increase in number over time [9-12]. In recent years, more than 8.5 million nonsurgical injection procedures have been performed annually worldwide, with botulinum toxin type A and hyaluronic acid filler injections being the first and second most common, respectively [13]. Hya-luronic acid (HA) is a linear anionic polysaccharide composed of repeating units of disaccharides D-glucuronic acid and N-acetyl-D-glucosamine linked together through alternating ß-1,3 and ß-1,4 glycosidic bonds [14-16]. It is a primary component of ex-tricellular matrix, vitreous humor, and synovial fluid of vertebrates [16,17]. Traditionally extracted from rooster combs, HA is now increasingly produced through microbial fermentation. Modifications of HA are relatively widespread, with cross-linking via hydroxyl and carboxyl groups being the most common one that influences the preven-tion of rapid degradation and provides long-term treatment effects [18].
Hyaluronic acid has been used in medicine for many years and has been implanted in millions of individuals in its native form as a highly biocompatible filling material, ex-ploiting both its physio-chemical characteristics as well as the biological properties of its cellular interactions [19,20]. In particular, the restorative power of hyaluronic acid and its ability to promote the proliferation and migration of fibroblasts by stimulating the neo-synthesis of collagen and other constituents of the extracellular matrix have been highly valued [21]. Multiple clinical trials have shown the effectiveness of a series of hyaluronic acids as dermal fillers in anti-wrinkle procedures and tissue regeneration [22,23]. The also,olidated use of this molecule has produced not only a considerable amount of clinical efficacy data but also significant evidence of excellent tolerability [24]. Based on its biological characteristics, hyaluronic acid is considered a real natural filler, and intradermal HA injections at the maximum concentration of 2% have shown no acute or chronic toxicity in several animal models [25,26]. HA is not immunogenic, does not induce any type of stabilization, does not interfere with the mechanisms of reproduction, and is not genotoxic, while its secondary effects are defined as minimal and negligible [27]. The HA at the center of this study, Foliage Intense, is obtained through a bacterial bio-fermentation process, which does not present any risk of contamination by anti-genic proteins; chemically cross-linked with BDDE (1,4-butanediol, diglyceryl ether); and stabilized with phosphate saline suspension buffer at pH 7.4 [19,28]. It has a lower molecular weight than the natural product, and its viscoelastic properties tend to be more viscous, showing a lower dissolution rate. The formulation thus stabilized demonstrates a long duration, while remaining biocompatible and injectable. In a comparative assessment, based on the scientific literature on similar medical devices, Foliage Intense has demonstrated equivalence to Restylane (produced by Q-Med) and Juvéderm_Ultra (Allergen) [29], both approved by the FDA and on the market for 20 years, and Belotero Intense and Belotero Volume (Merz Aesthetics) in terms of efficacy and safety [30,31].
1.2. Objectives of the study
1.2.1. Primary Objective
The main objective of this study is to assess the efficacy of Foliage Intense in correcting moderate and severe nasolabial folds using the Wrinkle Severity Rating Scale (WSRS) [32]. At each observation, the variations in the WSRS in the areas treated with Foliage Intense (FI) are compared with those in the areas treated with Belotero Intense (BI), aiming to demonstrate the non-inferiority of the investigated product. The effectiveness of the product will be assessed at the 6-month visit after the treatment (baseline treatment or after subsequent optional touch-up).
1.2.2. Secondary objectives
The secondary objectives of this study were (1) to evaluate the aesthetic result over time by using subjective evaluations such as the Wrinkle Severity Rating Scale (WSRS) [33] and the Global Aesthetic Improvement Scale (GAIS) [34], via both the subjects and the Evaluating Investigator; (2) to objectively evaluate the persistence of the product’s effects over time in the dermis via ultrasound of the soft tissue; (3) to objectively eval-uate the difference in volume over time using a 3D image system, VECTRA H2 (Can-field Scientific, Inc); (4) to analyze the subject’s views on all the treatment and out-comes as well as their overall satisfaction degree; (5) to assess the quality of the injec-tion by recording the judgment of the treating investigator with regard to the han-dling and efficacy of the product during the treatment visits; and (6) to assess the product's tolerability during the study, for allergies or other reactions that can occur as a result of the treatments. In addition, safety measures, including the presence and severity of injection site responses (ISRs), procedural pain assessment, and any adverse events (AEs), were assessed throughout the study.
2. Materials and Methods
2.1. Demographic characteristics of patients
All demographic data concerning all patients enrolled in this study are reported in Table 1.
Table 1: Demographic data of patients.
|
Variable |
Category |
Statistic |
All enrolled subjects (N=95) |
|
Gender |
Male |
n (%) |
4 (4.2%) |
|
Female |
n (%) |
91 (95.8%) |
|
|
Skin color |
I. Pale white skin or very light or Celtic |
n (%) |
3 (3.2%) |
|
II. Fair skin or European |
n (%) |
19 (20.0%) |
|
|
III. Darker white skin or dark European |
n (%) |
68 (71.6%) |
|
|
IV. Light brown skin |
n (%) |
5 (5.3%) |
|
|
Age (years) |
n |
95 |
|
|
Mean |
54.3 |
||
|
SD |
8.09 |
||
|
Minimum |
38 |
||
|
Median |
53 |
||
|
Maximum |
75 |
||
|
Height (cm) |
n |
95 |
|
|
Mean |
164.5 |
||
|
SD |
6.58 |
||
|
Median |
165 |
||
|
Maximum |
180 |
||
|
Weight (kg) |
n |
95 |
|
|
Mean |
62.5 |
||
|
SD |
9.8 |
||
|
Minimum |
46 |
||
|
Median |
60 |
||
|
Maximum |
95 |
||
|
Body mass index (kg/m2) |
n |
95 |
|
|
Mean |
23 |
||
|
SD |
3.07 |
||
|
Minimum |
17 |
||
|
Median |
22.8 |
||
|
Maximum |
33 |
2.2. Features of the devices
In this trial, a cross-linked hyaluronic resorbable acid filler named Foliage Intense 1x1ml, manufactured and distributed by Phitogen Holding S.p.A. (San Benedetto del Tronto, AP, Italy), is compared to Belotero Intense, manufactured by ANTEIS SA (Ge-neva, Switzerland), in order to correct both moderate and severe nasolabial folds. The two devices belong to Class III medical devices according to Annex VIII of the Regula-tion (EU) 2017/745 on Medical Devices and will be used comparatively on the same subjects through a split-face model. Foliage Intense (FI) 1x1mL is a class III, intrader-mal, resorbable medical device (sterile, apyrogenic, and physiological gel) used as a remedy for the correction of medium and deep skin sagging and for increasing the volume and contour of the lips (Phitogen Holding Spa, 2020).
2.3. Comparator
Belotero Intense® (BI) is an injectable resorbable implant indicated to fill deep wrin-kles and folds, as well as to restore and enhance soft tissue volume (contours of the face, lip volume, etc.). It is also suitable for the correction of facial atrophic scars. It is a sterile, non-pyrogenic, viscoelastic, colorless, transparent cross-linked sodium hyalu-ronate gel of non-animal origin in a physiological phosphate buffer. Composition: The main component is cross-linked sodium hyaluronate, of non-animal origin (in a con centration of 25.5 mg/ml), which is stabilized in a phosphate buffer with pH=7 and is injected intradermally using 27G½ needles. It is stored between 2°C and 8°C.
2.4. Functional component
The main component of Foliage Intense is cross-linked hyaluronic acid. Hyaluronic acid is obtained through a bacterial bio-fermentation process, excluding any risk of contamination by antigenic proteins. It is cross-linked by the agent BDDE and stabi-lized with phosphate saline suspension buffer at pH 7.4. It has a molecular weight similar to endogenous hyaluronic acid and a concentration of 2.5%, which allows a uniform distribution of the product in the dermis. Furthermore, Foliage Intense does not contain tissues or their derivatives, as the hyaluronic acid originates from bacterial fermentation and does not contain substances or derivatives of human blood. Finally, the composition of the product does not include, as an integral part, any substance that could be considered a medicinal specialty when used separately. Considering the absence of lidocaine or any other anesthetic substance in the product, the manufacturer advises the use of local anesthetic before injection in order to guarantee the neces-sary comfort to the patient.
2.5. Clinical Procedures
Each subject was treated with both products according to a split-face model [35]. The left and right sides of the face were treated in a randomized, observer-blinded manner (subject- and evaluator-blinded) with Foliage Intense (FI) 1x1mL and Belotero Intense (BI; Figure 1), respectively. In general, skin imperfections are symmetrical, especially on people's faces. As a result, the comparisons performed between the two treatments in this study for everyone are fair. After the participants signed the informed consent form, were screened for all inclusion/exclusion criteria, and were randomized, injections of the two products were given by the treating investigator in the locations identified during the first baseline visit. For these reasons, patient randomization was not required in this study protocol.
2.6. Inclusion and Exclusion criteria
Subjects were eligible for inclusion in the investigation if they met all the following criteria:
- Male or female subjects aged 18 years or older.
- Subjects with fully visible and approximately symmetrical bilateral nasolabial wrinkles.
- Subjects with a score of 3 or 4 in the Wrinkle Severity Rating Scale (WSRS).
- Subjects willing to abstain from any other facial, plastic, or cosmetic procedure below the level of the lower orbital rim for the duration of the study.
- Subjects willing to abstain from any exposure of their face to strong UV irradiation (UV session and/or sunbathing) during the entire duration of the study, without appropriate sun protection.
- Women of childbearing potential (WOCBP) agreeing to use means of contraception throughout the duration of the trial.
- Subjects with capacity to understand and sign a written informed consent form (ICF), which must be obtained prior to the initiation of study procedures.
- Subjects with ability and availability to return to the study site for the post-procedural fol-low-up examinations.
Subjects who met any of the following exclusion criteria were not enrolled in the study:
- Subjects with a score ≤2 or equal to 5 on the Wrinkle Severity Rating Scale (WSRS).
- Subjects who have received any previous facial cutaneous treatment for aesthetic correction (biomaterial implant, lifting, botulinum toxin injections, laser or ultrasound treatment, chemical facial peeling) within the 6 months prior to study inclusion.
- Subjects previously treated with permanent or semi-permanent filler(s).
- Subjects with a tendency to develop hypertrophic, atrophic, or keloid scars.
- Subjects with a clinically significant facial skin disease (infection, dermatitis, dermatosis, psoriasis, eczema, rosacea, herpes, etc.), that is chronic or currently active and which the investigator considers will adversely affect the areas to be examined in this trial.
- Subjects with facial volume deficiencies because of traumas or genetic defects.
- Subjects who present facial skin allergies, infections, or inflammation close to the inter-vention area.
- Subjects who presented with allergy or hypersensitivity to the study product or one of the ingredients of the formulation.
- Subjects suffering from neoplasia and/or from serious clinical conditions such as cardio-vascular disease, hepatic, pulmonary, neurological, renal, autoimmune or other conditions that, according to the investigator, preclude participation of the subjects in the study.
- Subjects in current treatment with antithrombotic and/or immunosuppressant agent(s) or taking these agents(s) within the preceding 1 week from study inclusion.
- Subjects who had taken aspirin, NSAIDs, or high doses of vitamin E within the preceding 1 week from study inclusion.
- Female subjects known to be pregnant or breastfeeding.
- Subjects enrolled in another clinical trial within the 4 weeks preceding the study or plan-ning to participate in another trial during the study in question.
The volume to be injected is at the discretion of the treating investigator depending on the width, length, and depth of the NLF, with the condition that the maximum vol-ume is 1.0mL. In all cases, the injected volume of both the investigated product and the comparator were equal. After 4 weeks, the subjects returned to perform the first safety check visit. When the subject did not present a complete aesthetic improvement on both folds, a secondary injection was performed (optional touch-up), if deemed necessary by the treating investigator, to ensure satisfactory correction in the treatment area. The subjects underwent touch-up treatment, in both nasolabial folds, according to the randomization list from the initial injection. The individuals who underwent the optional touch-up returned 30 days later for a second safety check visit. The next follow-up visit was scheduled 3 months after the last treatment (either the initial treatment or the optional touch-up). The subjects returned to month 6 after the last treatment for the evaluation of the primary efficacy endpoint. The following checks were provided at 9 months and then at 12 months after the last treatment (either the initial treatment or the touch-up), for the evaluation of the secondary endpoints and follow-up. An ultrasound of the treated areas was performed before the injection and after 1, 3, 6, 9, and 12 months to test the variation in the thick-ness of the soft tissues. The improvements in the Wrinkle Severity Rating Scale (WSRS) [32] and Global Aesthetic Improvement Scale (GAIS) [36] were assessed at each visit to evaluate changes in the nasolabial fold volume from baseline. In addition, the subjects were photographed to more objectively assess the changes over time in the NLFs, using a 3D imaging system (Vectra H2), which calculated the differences in terms of the volume over time. The treating investigator gave his opinion on the quality of the injection, and each subject confirmed their satisfaction with the product through a structured scale. A maximum of seven (7) visits were made throughout the study, depending on whether the subjects underwent touch-up, according to the scheme presented in Figure 2.
The performance evaluation of the study treatment was performed according to quantitative analysis criteria and the satisfaction of the patients/investigators as reported in the following sections. The blinded, independent expert medical professional (Evaluating Investigator) performed the observations and evaluations. Standard conditions for the treatment performance evaluations were as follows:
- Four hours before the study visit, subjects should avoid smoking and the consumption of coffee or alcohol.
- Two hours before each visit, the subjects should avoid the application of any cosmetic product on the skin test areas. All study evaluations should be per-formed at room temperature (no temperature/humidity recording is required).
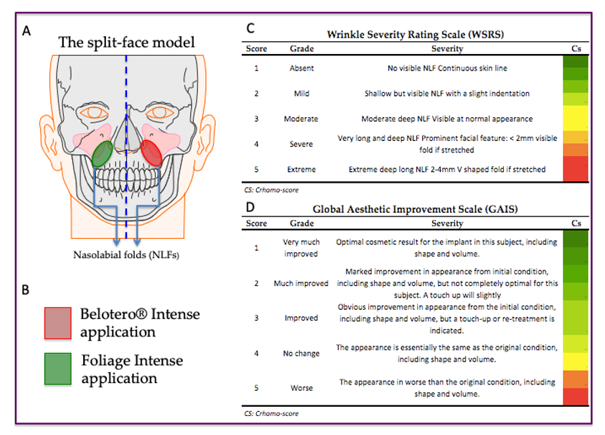
Figure 1: A) Split-face model representation showing the areas of application; B) Colors -associated Belotero and Foliage treatments; C) WSRS score evaluation scale; D) GAIS score evaluation scales.
2.7. Scores
2.7.1. Wrinkle Severity Rating Scale (WSRS)
The WSRS parameter is a 5-level system for assessing nasolabial folds, ranging from 1 (absent) to 5 (extreme). The Evaluating Investigator performed the evaluation via WSRS at screening (prior to treatment administration), after treatment administration, and during all visits (Day DJ. et. al, 2004).
2.7.2. Global Aesthetic Improvement Scale (GAIS)
GAIS is a 5-grade subjective test for performance analysis. The Evaluating Investigator evaluated the aesthetic improvement in the subjects’ nasolabial folds using a 5-point scale from 1 (very much improved) to 5 (worse). Aesthetic improvement was assessed using GAIS starting from the second visit and during all the study visits (Thomas, J.A. and Walker, P., 2010).
2.8. Product persistence overtime assessment through Ultrasound
The persistence over time of the product was assessed using ultrasound at the treatment visits and at every follow-up visit, measuring dermal thickness before treatment and at all control visits, until month 12. The product was considered reabsorbed when the thickness was like the basic measurement, i.e., the measurement before in-junction.
2.9. Evaluation of subject’s satisfaction
The subjects’ satisfaction was assessed during all visits using a Numerical Rating Scale from 1 to 5 (where 1 indicates high satisfaction with the product and 5 represents dissatisfaction).
2.10. Evaluation of injection satisfaction
The degree of satisfaction with the quality of the injection was assessed at the baseline visit and on the optional touch-up visit, after treatment, using a 0-4 Numerical Rating Scale, where 0 = no satisfaction and 4 = maximum satisfaction. The assessment was based on the handling of the product (viscosity, extrusion force, smoothness of injec-tion, lumpiness, etc.), according to the following categories: bad, sufficient, poor, good, or excellent.
2.11. Evaluation of product tolerability
The product's tolerability was evaluated by a means of an electronic diary filled out by the patient for two weeks after treatment and during all the study visits to assess al-lergies or other reactions that can occur as a result of the treatments (pain, erythema, edema, ecchymosis, pruritus, etc.), and any other adverse events, even systemic, that could have possibly occurred during the investigation. Each reaction was associated with a score: 0: none; 1: mild; 2: moderate; 3: severe.
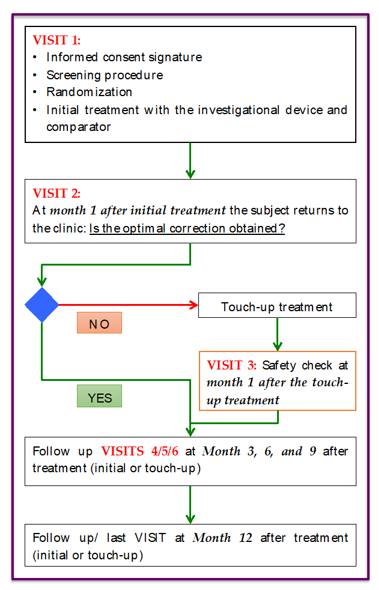
Figure 2: Flowchart representing the clinical procedure and the fol-low-up visit of patients.
3. Results
3.1. Summary of populations
Ninety-five subjects were enrolled and randomized, and they all received an injection on both treatment sides. One (1) did not return after visit V1, twelve (12) after visit V2, three (3) after visit V3, thirteen (13) after visit V4, twenty (20) after visit V5, and four-teen (14) after visit V6, resulting in a total of sixty-three (63/95; 66.3%) withdrawn sub-jects. A total of thirty-two subjects (32) (33.7%) completed the study, and were there-fore present at visit V7, of which twenty-two (22) completed all visits (with the exception of the optional V3 visit for those who did not receive the touch-up). Sixty-four (64) (67.4%) subjects completed visit V5, essential for the analysis of the primary endpoint. Using the formula for calculating statistical power, we found that including 64 subjects in the analysis is sufficient to achieve a power of 73% with an uncertainty index of 2%. Table 2 reports all data concerning the population distribution on the visits.
Table 2: Summary of populations.
|
Visit |
Subject descriptions |
Parameters |
Population |
||
|
N |
% |
||||
|
Screening |
V0 |
Screened subjects |
95 |
Enrolled |
|
|
Baseline |
V1 |
Screening failures |
0 |
||
|
Subjects randomized and treated |
95 |
100.00% |
Randomized |
||
|
1st check /Optional touch-up |
V2 |
Subject lost from V2 |
1 |
1.10% |
|
|
Subjects who skipped visit V2 |
3 |
3.20% |
|||
|
Subjects completed V2 visit |
91 |
95.80% |
|||
|
2nd check / Post touch-up |
V3 |
Subject lost from V3 |
12 |
||
|
Total subjects lost up to V3 |
13 |
13.70% |
|||
|
Subjects who skipped visit V3 |
1 |
1.10% |
|||
|
Subjects who skipped V3 because optional |
47 |
49.50% |
|||
|
Subjects who completed V3 visit |
34 |
35.80% |
|||
|
Follow-up |
V4 |
Subject lost to follow-up from V4 |
3 |
||
|
Total subjects lost up to V4 |
16 |
16.80% |
|||
|
Subjects who skipped visit V4 |
9 |
9.50% |
|||
|
Subjects who completed V4 visit |
70 |
73.70% |
|||
|
Efficacy visit |
V5 |
Subject lost to follow-up from V5 |
13 |
||
|
Total subjects lost up to V5 |
29 |
30.50% |
Safety, ITT |
||
|
Subjects who skipped visit V5 |
2 |
2.10% |
Safety, ITT |
||
|
Subjects who completed V5 visit |
64 |
67.40% |
Safety, ITT, PP |
||
|
Follow-up |
V6 |
Subject lost to follow-up from V6 |
20 |
||
|
Total subjects lost up to V6 |
49 |
51.60% |
|||
|
Subjects who skipped visit V6 |
6 |
6.30% |
|||
|
Subjects who completed V6 visit |
40 |
42.10% |
|||
|
Last follow-up |
V7 |
Subject lost to follow-up at V7 |
14 |
||
|
Total subjects lost up to V7 |
63 |
66.30% |
|||
|
Subjects who completed V7 visit |
32 |
33.70% |
|||
The number of subjects included in the Safety, ITT, and PP populations is presented in Table 3 below. A total of 95 subjects were screened, randomized, and treated; safety and efficacy were analyzed in all (100%) ITT subjects and 64 (67.4%) PP subjects (Table 3).
Table 3: Distribution of populations.
|
Type of Subjects |
Number |
Percentage |
|
Number of subjects recruited |
95 |
100% |
|
Number of subjects enrolled |
95 |
100% |
|
Number of subjects randomized |
95 |
100% |
|
Number of subjects receiving an injection on both treatment sides |
95 |
100% |
|
Number of subjects in Safety population |
95 |
100% |
|
Number of subjects in ITT population |
95 |
100% |
|
Number of subjects returning at visit V5 |
64 |
67.40% |
|
Number of subjects with major deviation |
0 |
0% |
3.2. WSRS score analyses after 6 months of treatment
3.2.1. PP population
Sixty-four subjects present at both the screening and V5 visit (six months after treatment) were included in the PP analysis. In this analysis, the changes from baseline in WSRS scores at 6 months were -0.50±0.13 in the Foliage Intense group and -0.48±0.12 in the belter intense group, both of which were highly significant according to the Wil-Coxon signed-rank test (p<0.001). Since the reduction in the two treatment groups is very similar, the comparison between the two treatments was not statistically significant based on the Wilcoxon signed-rank test (Figure 3).
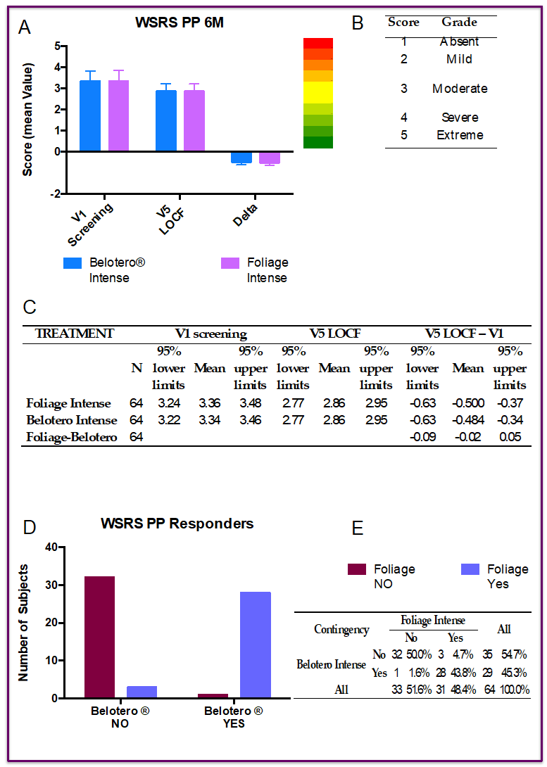
Figure 3: WSRS analyzed in Per Protocol population (PP): A) Six months after treatments (p<0.001). B) Chromo-score and WSRS parameter grades. C) Statistics of both treatments at V1, V5, and delta equal of V5-V1. D) Distribution of PP responders. E) Contingency table of responders (chi-square test: p<0.0001).
3.2.2. ITT population
All 95 randomized subjects were included in the ITT population.
Of these 95 subjects, 31 did not return to the visit at 6 months (V5), so the WSRS score from the previous V2, V3, or V4 visits was used as the WSRS score according to the LOCF procedure. In the ITT analysis, the changes from baseline in WSRS scores at 6 months were -0.73±0.14 in the Foliage Intense group and -0.72±0.13 in the Belotero In-tense group, both of which were determined to be highly significant using the Wilcoxon signed-rank test (p<0.001). Since the reduction in the two treatment groups is very similar, the comparison between the two treatments was not found to be statistically significant with the Wilcoxon signed-rank test (Figure 4).
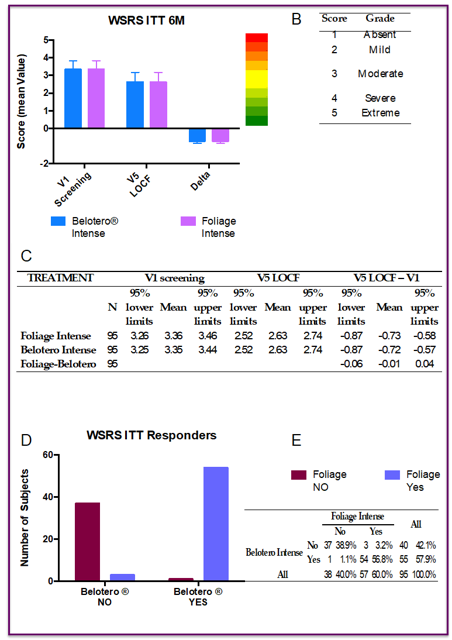
Figure 4: WSRS analyzed in Intention to Treat population (ITT): A) Six months after treatments (p<0.001). B) Chromo-score and WSRS parameter grades. C) Statistics of both treatments at V1, V5, and delta equal of V5-V1. D) Distribution of ITT responders. E) Contingency table of responders (chi-square test: p<0.0001).
3.2.3. Responder Analysis
The proportion of subjects with ≥ 1 grade improvement in WSRS from baseline at 6 months in the PP population was 45.3% and 48.4% in the Belotero Intense (BI) and Foli-age Intense (FI) groups, respectively. There were three responders in the Foliage Intense group who did not respond to Belotero Intense, while one subject responded to Belotero Intense but not Foliage Intense. Furthermore, the results of McNemar's test were not significant. The proportion of subjects in the ITT population with ≥ 1 grade improvement in WSRS from baseline at 6 months was 57.9% and 60.0% in the Belotero Intense (BI) and Foliage Intense (FI) groups, respectively. Furthermore, there were three Foliage Intense responders who were not Belotero Intense responders; vice versa, one subject responded to Belotero Intense but not Foliage Intense. Also in this case, the results of McNemar's test were not significant. However, the positive differences between FI and BI ranged between 2% and 3% in favor of the FI treatment (Figures 1E and 2E).
3.3. WSRS Scores across each follow-up section
Table 4 summarizes the data on the Wrinkle Severity Rating Scale (WSRS) score, where the “WSRS score” columns show the average scores with confidence limits of the WSRS at each visit. Their differences compared to the screening visit (Vx – Screening) are re-ported in the second column. The variations compared to the screening visit are reported in the second column as the "Belotero - Foliage" treatments. The reduction in WSRS was greater in the Foliage group compared to the group that received Belotero both immediately after the injections at baseline (-1.58 vs -1.41) and at touch-up (-1.86 vs -1.62). Differences between treatments were statistically significant according to the Wilcoxon signed-rank test (p=0.0007 at V1 and 0.0039 at V2). In subsequent follow-up visits (V3-V7), this difference disappeared and the two treatment groups were almost identical (Table 4).
Table 4: WSRS analyses comparing both treatments at different visits.
|
VISIT |
STATISTIC |
WSRS score |
Vₓ - Screening |
Belotero - |
p |
||
|
Belotero Intense |
Foliage Intense |
Belotero Intense |
Foliage Intense |
||||
|
V1 |
95% LCL |
3.25 |
3.26 |
||||
|
Mean |
3.35 |
3.36 |
|||||
|
95% UCL |
3.44 |
3.46 |
|||||
|
V1 |
95% LCL |
1.82 |
1.66 |
-1.55 |
-1.73 |
-0.26 |
|
|
Mean |
1.94 |
1.78 |
-1.41 |
-1.58 |
-0.17 |
0.0007 |
|
|
95% UCL |
2.05 |
1.90 |
-1.28 |
-1.43 |
-0.08 |
||
|
V2 |
95% LCL |
2.11 |
2.06 |
-1.28 |
-1.33 |
-0.14 |
|
|
Mean |
2.23 |
2.18 |
-1.13 |
-1.20 |
-0.07 |
ns |
|
|
95% UCL |
2.35 |
2.29 |
-0.99 |
-1.06 |
0.01 |
||
|
V2 |
95% LCL |
1.65 |
1.41 |
-1.80 |
-2.07 |
-0.39 |
|
|
Mean |
1.81 |
1.60 |
-1.62 |
-1.86 |
-0.24 |
0.0039 |
|
|
95% UCL |
1.97 |
1.78 |
-1.44 |
-1.64 |
-0.09 |
||
|
V3 |
95% LCL |
1.54 |
1.54 |
-1.93 |
-1.98 |
-0.19 |
|
|
Mean |
1.71 |
1.71 |
-1.71 |
-1.74 |
-0.03 |
ns |
|
|
95% UCL |
1.87 |
1.87 |
-1.49 |
-1.49 |
0.13 |
||
|
V4 |
95% LCL |
2.12 |
2.13 |
-1.25 |
-1.26 |
-0.08 |
|
|
Mean |
2.23 |
2.24 |
-1.10 |
-1.10 |
0.00 |
ns |
|
|
95% UCL |
2.34 |
2.35 |
-0.95 |
-0.94 |
0.08 |
||
|
V5 |
95% LCL |
2.77 |
2.77 |
-0.63 |
-0.63 |
-0.09 |
|
|
Mean |
2.86 |
2.86 |
-0.48 |
-0.50 |
-0.02 |
ns |
|
|
95% UCL |
2.95 |
2.95 |
-0.34 |
-0.37 |
0.05 |
||
|
V6 |
95% LCL |
2.95 |
2.95 |
-0.52 |
-0.55 |
-0.14 |
|
|
Mean |
3.05 |
3.05 |
-0.33 |
-0.35 |
-0.02 |
ns |
|
|
95% UCL |
3.15 |
3.15 |
-0.13 |
-0.15 |
0.09 |
||
|
V7 |
95% LCL |
2.47 |
2.47 |
-1.08 |
-1.09 |
-0.13 |
|
|
Mean |
2.69 |
2.69 |
-0.78 |
-0.78 |
0.00 |
ns |
|
|
95% UCL |
2.90 |
2.90 |
-0.48 |
-0.47 |
0.13 |
||
Note: LCL=lower confidence level; UCL: upper confidence level; ns=no statistical differences.
3.4. Global Aesthetic Improvement Scale (GAIS): score analyses
All results concerning the GAIS analyses in the ITT population (six different aspects) are reported in the table below (Table 5). Significant differences were identified in the following parameters based on the scores obtained:
- Evaluating Investigator (EI, Table 5A). Differences between treatments were sta-tistically significant (p=0.0156) according to the Wilcoxon signed-rank test. In the other visits, this difference disappeared and the two treatment groups were al-most identical.
- The mean volume difference assessed by 3D imaging at the first check-up was 0.42 (CI 0.32-0.53) cc in the Foliage Intense group and 0.35 (CI 0.26-0.44) cc in the Belotero group. This difference between the treatments was statistically signifycant (ANOVA p=0.0342), while at other visits it was not (Table 5D).
- The degree of satisfaction of the Injectors was better in the Foliage group compared to the Belotero group, both immediately after the baseline injection (FI 3.75 vs BI 3.56) and at the touch-up visit (FI 3.71 vs BI 3.45). Differences between treatments were highly statistically significant according to the Wilcoxon signed-rank test (V1 p=0.0005 and V2 p=0.0039; Table 5E).
Table 5: GAIS analysis.
Table 5A: GAIS reported by Evaluating Investigator (EI)
|
Visits |
N |
Foliage Intense |
Belotero® Intense |
p |
||||
|
95% LCL |
Mean |
95% UCL |
95% LCL |
Mean |
95% UCL |
|||
|
V2 First check |
91 |
2.07 |
2.21 |
2.35 |
2.11 |
2.24 |
2.37 |
ns |
|
V2 Touch-up |
42 |
1.34 |
1.52 |
1.71 |
1.52 |
1.69 |
1.87 |
0.0156 |
|
V3 Optional check |
34 |
1.71 |
1.94 |
2.17 |
1.71 |
1.91 |
2.11 |
ns |
|
V4 Follow-up |
70 |
2.29 |
2.46 |
2.62 |
2.33 |
2.49 |
2.64 |
ns |
|
V5 Follow-up |
64 |
3.06 |
3.19 |
3.31 |
3.06 |
3.19 |
3.31 |
ns |
|
V6 Follow-up |
40 |
3.52 |
3.68 |
3.83 |
3.52 |
3.68 |
3.83 |
ns |
|
V7 Follow-up |
32 |
3.24 |
3.47 |
3.69 |
3.24 |
3.47 |
3.69 |
ns |
Table 5B: GAIS reported by subject.
|
Visits |
N |
Foliage Intense |
Belotero® Intense |
p |
||||
|
95% LCL |
Mean |
95% UCL |
95% LCL |
Mean |
95% UCL |
|||
|
V2 First check |
91 |
1.89 |
2.04 |
2.2 |
1.89 |
2.04 |
2.2 |
ns |
|
V2 Touch-up |
42 |
1.49 |
1.69 |
1.89 |
1.52 |
1.71 |
1.91 |
ns |
|
V3 Optional check |
34 |
1.55 |
1.79 |
2.03 |
1.57 |
1.79 |
2.02 |
ns |
|
V4 Follow-up |
70 |
2.28 |
2.43 |
2.58 |
2.3 |
2.44 |
2.59 |
ns |
|
V5 Follow-up |
64 |
3.01 |
3.14 |
3.27 |
3.01 |
3.14 |
3.27 |
ns |
|
V6 Follow-up |
40 |
3.31 |
3.48 |
3.64 |
3.31 |
3.48 |
3.64 |
ns |
|
V7 Follow-up |
32 |
3.2 |
3.41 |
3.61 |
3.2 |
3.41 |
3.61 |
ns |
Table 5C: Dermal thickness in mm assessed by ultrasound.
|
Visits |
N |
Foliage Intense |
Belotero® Intense |
p |
||||
|
95% LCL |
Mean |
95% UCL |
95% LCL |
Mean |
95% UCL |
|||
|
V1 Baseline |
95 |
1.13 |
1.31 |
1.49 |
1.12 |
1.3 |
1.48 |
ns |
|
V2 Touch-up |
41 |
1.1 |
1.36 |
1.61 |
1.15 |
1.4 |
1.65 |
ns |
|
V4 Follow-up |
62 |
0.86 |
0.94 |
1.02 |
0.87 |
0.95 |
1.03 |
ns |
|
V5 Follow-up |
64 |
0.68 |
0.71 |
0.74 |
0.68 |
0.71 |
0.74 |
ns |
|
V6 Follow-up |
39 |
0.64 |
0.67 |
0.69 |
0.62 |
0.65 |
0.69 |
ns |
|
V7 Follow-up |
17 |
0.63 |
0.67 |
0.71 |
0.57 |
0.62 |
0.66 |
ns |
Table 5D: Volume difference (cc).
|
Visits |
N |
Foliage Intense |
Belotero® Intense |
p |
||||
|
95% LCL |
Mean |
95% UCL |
95% LCL |
Mean |
95% UCL |
|||
|
V1 Baseline |
95 |
0.69 |
0.79 |
0.9 |
0.65 |
0.74 |
0.84 |
ns |
|
V2 First check |
91 |
0.32 |
0.42 |
0.53 |
0.26 |
0.35 |
0.44 |
0.0342 |
|
V2 Touch-up |
42 |
0.47 |
0.64 |
0.82 |
0.48 |
0.66 |
0.83 |
ns |
|
V3 Optional check |
34 |
0.24 |
0.42 |
0.6 |
0.2 |
0.36 |
0.53 |
ns |
|
V4 Follow-up |
70 |
0.04 |
0.13 |
0.23 |
-0.03 |
0.08 |
0.19 |
ns |
|
V5 Follow-up |
64 |
-0.21 |
-0.1 |
0.02 |
-0.29 |
-0.16 |
-0.02 |
ns |
|
V6 Follow-up |
40 |
-0.2 |
-0.03 |
0.15 |
-0.22 |
-0.06 |
0.1 |
ns |
|
V7 Follow-up |
32 |
-0.19 |
-0.02 |
0.15 |
-0.13 |
0.02 |
0.16 |
ns |
Table 5E: Subject’s overall satisfaction.
|
Visits |
N |
Foliage Intense |
Belotero® Intense |
p |
||||
|
95% LCL |
Mean |
95% UCL |
95% LCL |
Mean |
95% UCL |
|||
|
V2 First check |
91 |
1.63 |
1.76 |
1.88 |
1.64 |
1.77 |
1.89 |
ns |
|
V2 Touch-up |
42 |
1.18 |
1.36 |
1.54 |
1.2 |
1.38 |
1.56 |
ns |
|
V3 Optional check |
34 |
1.18 |
1.35 |
1.52 |
1.18 |
1.35 |
1.52 |
ns |
|
V4 Follow-up |
70 |
1.63 |
1.74 |
1.86 |
1.65 |
1.76 |
1.87 |
ns |
|
V5 Follow-up |
64 |
2.12 |
2.25 |
2.38 |
2.15 |
2.27 |
2.39 |
ns |
|
V6 Follow-up |
40 |
2.36 |
2.53 |
2.69 |
2.36 |
2.53 |
2.69 |
ns |
|
V7 Follow-up |
32 |
2.2 |
2.44 |
2.68 |
2.2 |
2.44 |
2.68 |
ns |
Table 5F: Injectors’ satisfaction.
|
Visits |
N |
Foliage Intense |
Belotero® Intense |
p |
||||
|
95% LCL |
Mean |
95% UCL |
95% LCL |
Mean |
95% UCL |
|||
|
V1 Baseline |
95 |
3.64 |
3.75 |
3.85 |
3.44 |
3.56 |
3.68 |
0.0005 |
|
V2 Touch-up |
42 |
3.52 |
3.71 |
3.91 |
3.22 |
3.45 |
3.68 |
0.0039 |
Note: GAIS analyzed in ITT population (secondary endpoints); Note: LCL=lower confidence level; UCL=upper confidence level. Significant statistical results are marked in bold text.
3.5. Safety and Tolerability
3.5.1. Adverse Events
In the 95 subjects treated with both Foliage Intense and belter Intense, no adverse events, neither serious nor non-serious, were reported.
3.5.2. Local tolerability
Five subjects reported cases of erythema, of which three were associated with both Be-looter Intense and Foliage Intense and two only with belter Intense. Four subjects experienced redness, of which three experienced it with both belter Intense and Fo-liege Intense and one only with belter Intense. Two subjects reported pain, of which one was associated with both belter Intense and Foliage Intense and one was associated with only belter Intense. All local events were mild, except for moderate-intensity redness on both sides in subject 01-028 and redness plus moder-rate-intensity pain on the side treated with belter in subject 01-016. No cases of edema or itching were reported. Of the patients with at least one local event, seven (7.4%) were treated with belter Intense for a total duration of 20 days and five (5.3%) were treated with Foliage Intense for a total duration of 12 days.
4. Discussion
Tissue filler injections remain one of the most performed cosmetic procedures [37-40]. In the most important meta-analysis on the topic in the literature, the authors systematized and presented the available data on the aesthetic outcomes and safety of clinical trials concerning the treatment of the nasolabial fold area with HA fillers [23]. The authors performed a systematic review of randomized clinical trials to obtain documents from the following online databases: MEDLINE [41], Science Direct [42], EMBASE [43], BIOSIS [44], SciELO [45], Scopus [46], Cochrane Controlled Register of Trials [47], and Web of Science [48]. The primary outcomes included aesthetic improvements measured using the Wrinkle Severity Rating Scale score [32] and the Global Aesthetic Improvement Scale [34]. Secondary outcomes were the incidence rates of complications occurring after the procedure. In this analysis, the pooled mean WSRS score was 3.23 (95% CI: 3.20–3.26) at baseline. One month after the procedure, the pooled WSRS score had reached 1.79 (95% CI: 1.74–1.83); after six months of treatment, it was 2.02 (95% CI: 1.99–2.05), and after 12 months it was 2.46 (95% CI: 2.4–2.52). Looking at the GAIS scores, one month after the procedure, the pooled GAIS score had reached 2.21 (95% CI: 2.14–2.28). After six months, it was 2.32 (95% CI: 2.26–2.37), and after 12 months, it was 1.27 (95% CI: 1.12–1.42). Overall, the pooled incidence of all complications was 0.58 (95% CI: 0.46–0.7). The most common complications included lumpiness (43%), tenderness (41%), swelling (34%), and bruising (29%) [23]. These calculations were performed based on a total of 50 different clinical trials and were considered a point of reference for the results included in this clinical study. The results of this study are very close to those reported in the large meta-analysis mentioned above [23]. Indeed, the trend of effectiveness could be confirmed. So far, the fillers used for treatment of the nasolabial fold area allow a satisfying and sustainable improvement to be achieved. The results presented in this study provide a comparison of two different fillers. There is one study in the literature in which 21 different HA-composed fillers were compared [49], but no data concerning WSRS and GAIS have been compared. A comparative as-assessment between Foliage Intense (FI) and belter Intense (BI) was previously published. Therefore, the primary endpoint hypothesis of this study, the non-inferiority of Foliage Intense (FI) in comparison with Belotero Intense (BI), was demonstrated through the WSRS scores at six months (V5). Indeed, in the PP population composed of 64 subjects, the 95% confidence limits of the difference between treatments ranged from -0.09 to 0.05, lower than the pre-set margin of error of 0.25. This result is also console-dated by the analysis of the ITT population (95 subjects), where the 95% confidence Limities of the difference between treatments were between -0.06 and 0.04. The proportion of responders (≥ 1 grade improvement in WSRS from baseline at 6 months) was 57.9% and 60.0% in the belter Intense and Foliage Intense groups, respectively. Here, these differences were in favor of Foliage but were not significant according to McNemar's test. Furthermore, when looking at the WSRS scores, the analyzed data are almost identical, not only at V5 but at all other follow-up visits, while immediately after the injections, the reduction in WSRS scores is statistically significantly greater with FI rather than with BI (p= 0.0007 at V1 and 0.0039 at V2 with the Wilcoxon signed-rank test). On the other hand, GAIS scores reported by the EI and the subjects are almost identical in the two treatment groups at all visits, except for a greater improvement in the GAIS score given by EI in the Foliage Intense group at visit V2 of touch-up (p=0.0156), where the two treatment groups did not differ regarding volume difference and dermal thickness. In addition, the two treatment groups did not differ regarding dermal thickness assessed via ultrasound or volume difference measured using a 3D image system. However, they differed in a statistically significant manner (ANOVA p=0.0342) at the first check according to the difference in volume: 0.42 (CI 0.32-0.53) cc and 0.35 (CI 0.26-0.44) cc in the FI and BI groups, respectively. Overall subject satisfaction was nearly identical for the two treatment groups at all visits, while injector satisfaction was better for Foliage compared to Belotero, in comparison with the baseline injection (p=0.0005) and after touch-up (p=0.0039). Furthermore, an analysis of the incidence of specific complications revealed that the most common were mild, transient, and reversible. These include lumpiness (43%), tenderness (41%), swelling (34%), bruising (29%), pain (28%), and redness (26%) [13,23,50,51]. More severe complications that could potentially lead to ire-reversible damage occurred very sporadically. The present cohort of patients revealed no heavy or complicated adverse events associated with HA administration, and the most common mild transient phenomenon was redness, present only in 4.21% of treatments.
5. Conclusions
The present study and the associated statistical analyses revealed no significant differences between FI and BI treatments. Both primary and secondary endpoints were achieved through adherence to the protocol established at the beginning of the study. In terms of the product’s safety, no adverse events, neither serious nor non-serious, were reported in the 95 subjects treated with both Foliage and Belotero. Furthermore, local events identified in the five subjects treated with Foliage were found to be of equal ex-tent and duration on the Belotero side in the split-face model. However, only two sub-jects had mild erythema, and one had moderate redness and moderate pain only on the side treated with Belter. It is important to note that no local events occurred on only the side of Foliage Intense application. Based on a recent extensive review of the literature, the main results in several studies are very close to those in the present study, especially regarding the 6-month results for WSRS, GAIS, and safety parameters.
Author Contributions
Conceptualization, M.R. and A.M.; methodology, M.R. and A.M.; software, A.M. and N.F.; validation, M.R., M.M., and N.F.; formal analysis, N.F.; investigation, M.R. and A.M.; resources, M.R. and M.M.; data curation, M.M. and N.F.; writing—original draft preparation, M.R. and N.F.; writing—review and editing, M.R. and N.F.; visualization, M.R., M.M., and N.F.; supervision, M.R.; project administration, M.M.; funding acquisition, M.R. and M.M.
Funding
This research received no external funding. Institutional Review Board Statement: The study was conducted in accordance with the Declara-tion of Helsinki and approved by the Ethical Committee for Clinical Trials of the Tuscany Region (CEAVNO) on November 21st, 2021 (studies involving humans; approval number: 20743).
Informed Consent Statement
Informed consent was obtained from all subjects involved in the study, according to the disposition of the Ethical Committee CEAVNO.
Data Availability Statement
All data obtained from this study are available by consultation with the authors (M.R; A.M.).
Conflicts of Interest
The authors declare no conflicts of interest.
References
- Kaminer MS, Avelar RL, Baumann L, et al. Long-Term Safety and Effectiveness of Cold-Crosslinked Hyaluronic Acid Fillers: Multicenter, Randomized, Controlled, Double-Blind Study. Aesthetic Surgery Journal (2025): sjaf080.
- Li Q, Cui H, Tseng F-W, et al. The Assessment, Strategy, and Treatment Protocol: Nasolabial Fold Assessment, Strategy, and Treatment With Hyaluronic Acid Fillers in Chinese Patients. Plastic and Reconstructive Surgery - Global Open 13 (2025): e6792.
- Nilforoushzadeh MA, Heidari-Kharaji M, Fakhim T, et al. Efficacy Evaluation of Endolift Laser for Treatment of Nasolabial Folds and Marionette Lines. Skin Research and Technology 29 (2023): e13480.
- Chung JH, Hanft VN, Kang S. Aging and Photoaging. Journal of the American Academy of Dermatology 49 (2003): 690-697.
- Rabe JH, Mamelak AJ, McElgunn PJS, et al. Photoaging: Mechanisms and Repair. Journal of the American Academy of Dermatology 55 (2006): 1-19.
- Fagien S, Monheit G, Jones D, et al. Hyaluronic Acid Gel With (HARRL) and Without Lidocaine (HAJU) for the Treatment of Moderate-to-Severe Nasolabial Folds: A Randomized, Evaluator-Blinded, Phase III Study. Dermatol Surg 44 (2018): 549-556.
- Monheit G, Beer K, Hardas B, et al. Safety and Effectiveness of the Hyaluronic Acid Dermal Filler VYC-17.5L for Nasolabial Folds: Results of a Randomized, Controlled Study. Dermatol Surg 44 (2018): 670-678.
- Shin J-W, Kwon S-H, Choi J-Y, et al. Molecular Mechanisms of Dermal Aging and Antiaging Approaches. IJMS 20 (2019): 2126.
- Myung Y, Jung C. Mini-Midface Lift Using Polydioxanone Cog Threads. Plastic and Reconstructive Surgery - Global Open 8 (2020): e2920.
- Fuente-del-Campo A, Lucchesi R, Ley MaDP C. Bidirectional Armed Needle: A Useful Surgical Tool in Plastic Surgery. Plastic & Reconstructive Surgery 100 (1997): 695-698.
- Yi K-H, Wan J, Yoon SE, et al. A Novel Approach for Facial Slimming Using Injectable Ascorbic Acid and Ferrous Gluconate: A Case Report. Journal of Craniofacial Surgery (2025).
- Han WY, Kim HJ, Kwon R, et al. Safety and Efficacy of Poly-L-Lactic Acid Filler (Gana V vs. Sculptra) Injection for Correction of the Nasolabial Fold: A Double-Blind, Non-Inferiority, Randomized, Split-Face Controlled Trial. Aesth Plast Surg 47 (2023): 1796-1805.
- Goodman GJ, Liew S, Callan P, et al. Facial Aesthetic Injections in Clinical Practice: Pretreatment and Posttreatment Consensus Recommendations to Minimise Adverse Outcomes. Aust J Dermatology 61 (2020): 217-225.
- Dicker KT, Gurski LA, Pradhan-Bhatt S, et al. Hyaluronan: A Simple Polysaccharide with Diverse Biological Functions. Acta Biomaterialia 10 (2014): 1558-1570.
- Necas J, Bartosikova L, Brauner P, et al. Hyaluronic Acid (Hyaluronan): A Review. Vet Med 53 (2008): 397-411.
- Rivas F, Erxleben D, Smith I, et al. Methods for Isolating and Analyzing Physiological Hyaluronan: A Review. American Journal of Physiology-Cell Physiology 322 (2022): C674-C687.
- Cowman MK, Lee H-G, Schwertfeger KL, et al. The Content and Size of Hyaluronan in Biological Fluids and Tissues. Front Immunol 6 (2015).
- Tiwari S, Bahadur P. Modified Hyaluronic Acid Based Materials for Biomedical Applications. International Journal of Biological Macromolecules 121 (2019): 556-571.
- Iaconisi GN, Lunetti P, Gallo N, et al. Hyaluronic Acid: A Powerful Biomolecule with Wide-Ranging Applications—A Comprehensive Review. IJMS 24 (2023): 10296.
- Balazs E. Hyaluronan as an Ophthalmic Viscoelastic Device. CPB 9 (2008): 236-238.
- Huynh A, Priefer R. Hyaluronic Acid Applications in Ophthalmology, Rheumatology, and Dermatology. Carbohydrate Research 489 (2020): 107950.
- Bukhari SNA, Roswandi NL, Waqas M, et al. Hyaluronic Acid, a Promising Skin Rejuvenating Biomedicine: A Review of Recent Updates and Pre-Clinical and Clinical Investigations on Cosmetic and Nutricosmetic Effects. International Journal of Biological Macromolecules 120 (2018): 1682-1695.
- Stefura T, Kacprzyk A, Droś J, et al. Tissue Fillers for the Nasolabial Fold Area: A Systematic Review and Meta-Analysis of Randomized Clinical Trials. Aesth Plast Surg 45 (2021): 2300-2316.
- Meçani R, Amiri M, Kadouch J, et al. Combined and Hybrid Treatments of Hyaluronic Acid (HA) and Calcium Hydroxylapatite (CaHA): A Systematic Review of Mechanisms of Action, Aesthetic Effectiveness, Satisfaction, and Safety Profile. Aesth Plast Surg (2025).
- Kim MJ, Seong K-Y, Kim DS, et al. Minoxidil-Loaded Hyaluronic Acid Dissolving Microneedles to Alleviate Hair Loss in an Alopecia Animal Model. Acta Biomaterialia 143 (2022): 189-202.
- Salinas-Alvarez Y, Quiroga-Garza A, Soto-Dominguez A, et al. In Vivo Models for the Study of Hyaluronic Acid Fillers: A Review. Aesth Plast Surg 47 (2023): 1185-1191.
- El-Khalawany M, Fawzy S, Saied A, et al. Dermal Filler Complications: A Clinicopathologic Study with a Spectrum of Histologic Reaction Patterns. Annals of Diagnostic Pathology 19 (2015): 10-15.
- Mao Z, Shin H-D, Chen R. A Recombinant E. Coli Bioprocess for Hyaluronan Synthesis. Appl Microbiol Biotechnol 84 (2009): 63-69.
- La Medicina Estetica. Congresso SIME 39.
- Ducher G, Prasetyo AD, Rubin MG, et al. Hyaluronic Acid Fillers with Cohesive Polydensified Matrix for Soft-Tissue Augmentation and Rejuvenation: A Literature Review. CCID 9 (2016): 257-280.
- Park KE, Mehta P, Kherani F, et al. Response of 21 Hyaluronic Acid Fillers to Recombinant Human Hyaluronidase. Plastic and Reconstructive Surgery - Global Open 11 (2023): e5457.
- Day DJ, Littler CM, Swift RW, et al. The Wrinkle Severity Rating Scale: A Validation Study. American Journal of Clinical Dermatology 5 (2004): 49-52.
- Day DJ, Littler CM, Swift RW, et al. The Wrinkle Severity Rating Scale: A Validation Study. American Journal of Clinical Dermatology 5 (2004): 49-52.
- Narins RS, Brandt F, Leyden J, et al. A Randomized, Double-Blind, Multicenter Comparison of the Efficacy and Tolerability of Restylane Versus Zyplast for the Correction of Nasolabial Folds. Dermatol Surg 29 (2003): 588-595.
- Priya D, Patil S. A Split Face Comparative Interventional Study to Evaluate the Efficacy of Fractional Carbon Dioxide Laser against Combined Use of Fractional Carbon Dioxide Laser and Platelet-Rich Plasma in the Treatment of Acne Scars. Indian Dermatol Online J 14 (2023): 371.
- Callan P, Halstead M, Rogers, et al. Efficacy and Safety of a Hyaluronic Acid Filler in Subjects Treated for Correction of Midface Volume Deficiency: A 24-Month Study. CCID 6 (2013): 81.
- Fundarò SP, Salti G, Malgapo DMH, et al. The Rheology and Physicochemical Characteristics of Hyaluronic Acid Fillers: Their Clinical Implications. IJMS 23 (2022): 10518.
- Murthy R, Roos JCP, Goldberg RA. Periocular Hyaluronic Acid Fillers: Applications, Implications, Complications. Current Opinion in Ophthalmology 30 (2019): 395-400.
- Signorini M, Liew S, Sundaram H, et al. Global Aesthetics Consensus: Avoidance and Management of Complications from Hyaluronic Acid Fillers—Evidence- and Opinion-Based Review and Consensus Recommendations. Plastic & Reconstructive Surgery 137 (2016): 961e-971e.
- Trinh LN, Gupta A. Hyaluronic Acid Fillers for Midface Augmentation: A Systematic Review. Facial Plast Surg 37 (2021): 576-584.
- Https://Pubmed.Ncbi.Nlm.Nih.Gov.
- Https://Www.Sciencedirect.Com.
- Https://Www.Embase.Com/Landing?Status=grey.
- Https://Www.Ebsco.Com/It-It/Prodotti/Banche-Dati-per-La-Ricerca/Biosis-Previews.
- Scielo.Org.
- Https://Www.Scopus.Com/Home.Uri.
- Https://Www.Cochranelibrary.Com/Central.
- Https://Clarivate.Com/Academia-Government/Scientific-and-Academic-Research/Research-Discovery-and-Referencing/Web-of-Science/.
- Park KE, Mehta P, Kherani F, et al. Response of 21 Hyaluronic Acid Fillers to Recombinant Human Hyaluronidase. Plastic and Reconstructive Surgery - Global Open 11 (2023): e5457.
- DeLorenzi C. Complications of Injectable Fillers, Part 2: Vascular Complications. Aesthetic Surgery Journal 34 (2014): 584-600.
- Callan P, Halstead M, Rogers, et al. Efficacy and Safety of a Hyaluronic Acid Filler in Subjects Treated for Correction of Midface Volume Deficiency: A 24 Month Study. CCID 6 (2013): 81.