Alberto Baldelli1,2,3, Andrew Poznikoff3, Nicholas West5, Jeffrey N. Bone5, Matthias Görges3,5, Robert Purdy3,4,5*
1School of Agriculture and Food Sustainability, University of Queensland, Brisbane, Australia
2Queensland Alliance for Agriculture and Food Innovation, University of Queensland, Brisbane, Australia
3Department of Anesthesiology, Pharmacology & Therapeutics, University of British Columbia (UBC), Vancouver, BC, Canada
4Department of Anesthesia, BC Children’s Hospital, Vancouver, BC, Canada
5Research Institute, BC Children’s Hospital, Vancouver, BC, Canada
*Corresponding Author: Robert Purdy, Pediatric Anesthesia Research Team, BC Children Hospital; Room T3-246 - 4480 Oak Street, Vancouver, BC V6H 3V4, Canada.
Received: 22 September 2026; Accepted: 29 September 2026; Published: XX- October 2026
The neonicotinoid imidacloprid (IMI) is widely used in agriculture and gardening and it has been found to cause harmful effects on the reproductive health of non-target animals. The aim of this study was to evaluate the effects of IMI on the body mass, testes mass, blood vessels, histology, and reactive oxygen species (ROS) of the male Wistar rat testes. Rats were orally administered IMI at doses of 2 or 8 mg/kg body mass/ day for 60 days. These doses were selected based on the NOAEL dose. The body mass of rats was recorded twice a week during treatment; after euthanasia, tests were collected and their mass was measured with a scale. We examined the macroscopic appearance of blood vessels in rat tests and analyzed histological changes. Levels of ROS were determined with diclorodihidrofluorescein diacetate (DCFH-DA). No significant changes in body mass or testes mass were observed in the Wistar rats compared with the control group. ROS levels were increased in control and 2 mg/ body mass/day groups however, we found a decrease in the 8 mg/body mass/day group. We also observed severe damage to blood vessels and testicular tissue, with blood vessels exhibiting pathological dilation in experimental groups, contributing to altered ROS levels in spermatozoa and, consequently, their fertilizing capacity. The relationship between blood vessel damage, spermatogenesis, and ROS requires in-depth investigation through molecular studies to support stricter regulation of this insecticide's use, given the harm it causes to animal and human health, as well as the environment.
Neonicotinoid; Imidacloprid; Blood Vessel; Reactive Oxygen Species; Testes, Spermatozoa; Toxicology
Intubation articles; Isolation Chamber articles
Introduction
Aerosol-generating medical procedures (AGMP), including endotracheal intubation, preoxygenation, and bag-mask ventilation, can increase the risk of healthcare provider exposure to aerosolized severe acute respiratory syndrome coronavirus 2 (SARS-CoV-2) (1-5). Over the past four years, several plexiglass boxes were described that covered a patient’s head and shoulders, providing a physical barrier between the patient and the healthcare providers during AGMP (6). Multiple trials and reviews have highlighted concerns with using these boxes, including breaches in personal protective equipment (PPE), increased intubation attempts, and prolonged intubation time (7-16). In addition, while most boxes provided adequate protection against droplet contamination, some could increase provider exposure to aerosols (10) (12, 13) (17). There are no reports of the barriers altering response time to emergencies. The rationale for this study was to evaluate a novel negative pressure isolation chamber (NPIC) developed to overcome some of the design concerns of previous devices. The primary outcome was to determine if the use of the NPIC significantly prolonged intubation time. Secondary outcomes included measuring the delay in other key airway management tasks, such as endotracheal tube (ETT) securement and diagnosis of an airway emergency, quantifying the concentration of aerosols at the location of the healthcare provider, and evaluation of user experience with the NPIC. We believe that the benefits and risks of an isolation chamber must be clearly documented in a simulation trial before clinical trials are contemplated.
Methods
Study design and approval
We conducted a within-subject, block-randomized, simulated procedure evaluation study, with anesthesiology staff as participants, to compare the performance of key intubation tasks with and without the NPIC and to analyze the concentrations of aerosols released during these procedures in an operating room setting using a high-realism adult intubating manikin. Ethical approval was obtained from the University of British Columbia Children’s & Women’s Research Ethics Board (H20-01665; date of approval 2020-09-22; PI: R Purdy). This manuscript follows the Consolidated Standards of Reporting Trials (CONSORT) guidelines (18).
Participants
We recruited pediatric anesthesiologists and fellows at BC Children’s Hospital (BCCH) between 2020-09-30 and 2020-10-27. Participants were recruited via electronic communication and distributed to the entire anesthesia department, as well as posters in common spaces. We enrolled the first twenty eligible participants who responded. Participation was voluntary and did not impact employment status or performance review. Informed, written consent was obtained.
Investigational device
The NPIC is an isolation chamber used during intubation (Figure 1). The modular design allows for the variable positioning of armports to accommodate patients of different ages and sizes. The interchangeable panels allow rapid assembly and facilitate cleaning and storage. There are 4-6 armports, sealed with disposable arm sleeves when in use, positioned at the front and sides of the chamber to allow access to the patient. The positioning of the air extraction and inlet ports directs airflow over the patient’s face and head, optimizing aerosol capture and extraction. There is a 2” extraction port for attachment of a high flow (>900 lpm) extraction fan and optional 7/8” air extraction ports that accept standard inline anesthesia circuit filters (N95 and N99), allowing attachment of wall suction or smoke evacuator tubing.
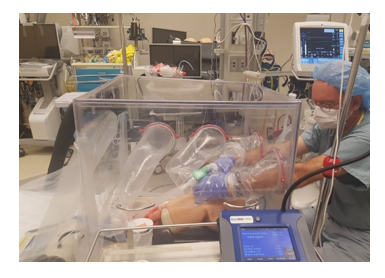
Figure 1: An anesthesiologist utilizes the Negative Pressure Airway Chamber to preoxygenate the intubation manikin.
Experimental setting and equipment
The simulation experiment was conducted in the BCCH anesthesia induction room using an Airsim Advanced Bronch X manikin (Trucorp, United Kingdom). An adapted patient warmer (Bair Hugger™ Normothermia System, 3M, Saint Paul, MN) was used as a source of high-flow suction and connected to the distal end of the NPIC. A saline nebulizer (VIXONE Nebulizer Mask Kit, Westmed, Tucson, AZ) was connected to one bronchus of the manikin to generate aerosols. Particulate matter was detected using a Dusttrak DRX aerosol monitor 8533 (TSI Inc., Shoreview, USA), positioned on an IV pole placed 90 cm above the bed in line with the top left corner of the NPIC; the Dusttrak monitor records particulate matter in the range 0.3-10 µm.
Experimental conditions
All participants performed one trial with and one without the NPIC. The order in which each participant performed these trials was randomized to control for learning effects. Before recruitment started, the research manager created a randomization schedule using Excel’s (Microsoft, United States) random number function, with an allocation ratio (with NPIC first: without NPIC first) of 1:1 and a block size of 10. Participants were informed of their allocation after their practice sessions to minimize potential planning time before the first trial.
Study procedures
Each participant completed a pre-trial questionnaire, which included demographic questions on sex, height, use of eyeglasses, whether they felt adequately rested, provider type (staff or fellow), and years of practice, as well as questions on previous experience with and perception of protective barriers during intubation. Before the full simulation, the participant used indirect laryngoscopy (Glidescope, Verathon Inc. USA) for two practice intubations without and two with the NPIC. Participants chose their preferred glove size, eye protection, equipment placement, and bed height before each timed trial. A research team member acted as an assistant, aiding with initiating the simulated induction, removing the stylet after ETT placement, and holding the ETT during securing. The assistant also helped remove the NPIC when required. Participants donned PPE following the practice sessions and before the timed trials. PPE included an isolation gown, surgical gloves, eye protection, and a surgical mask to conserve N95 mask supplies. For each trial (Figure 2), an oxygen flow rate of 10 L/min was started through the saline nebulizer to begin aerosol generation (TSTART). In trials utilizing the NPIC, the participants placed their hands into the NPIC sleeves and put latex gloves on top of the sleeve gloves to improve grip (TNPIC). The participant then performed preoxygenation with high-flow oxygen at 10 L/min for 3 minutes. After preoxygenation, the assistant simulated an induction over 30 seconds (end of 30 seconds marked as TINDUCTION), and the oxygen flow through the saline nebulizer was turned off. The participant then intubated the manikin (TINT-START), with completion confirmed visually by inflation of the manikin’s lungs (TINT-FINISH) and secured the ETT T(SECURE). A simulated emergency (desaturation) was announced (TDESAT-START), requiring the participant to ask for the removal of the NPIC if in use, place a stethoscope on the chest, and listen bilaterally for 10 seconds to simulate assessment of desaturation (the end of the 10-second auscultation was marked as TDESAT-DIAGNOSE). At the end of the first trial iteration, all equipment was reset by the research assistants before the second trial iteration. After each trial, the PPE of the participant and assistant were checked for breaches, and the NPIC was inspected to ensure a proper seal remained on the sleeves.
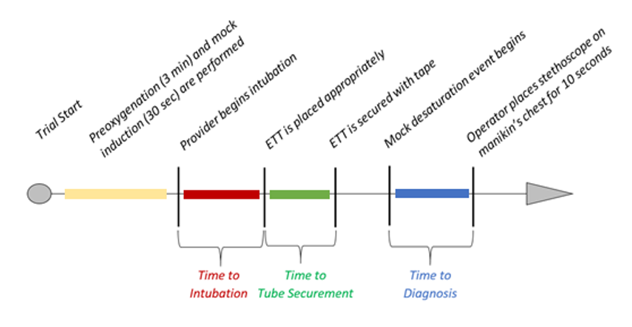
Figure 2: Timeline of key events denoting the main time periods of interest, including the time to intubation, time to tube securement, and time to diagnosis of the airway emergency.
After completing both trial conditions, each participant completed a post-study questionnaire to provide feedback on their experience using the NPIC. The survey included the following questions: 1) Did the use of the airway chamber make intubation more challenging? 2) Did the use of the chamber make pre-oxygenation more difficult? 3) Could arm position be improved? 4) Was visualization significantly impaired by the plexiglass? 5) Was putting on exam gloves inside the chamber difficult? 6) Was the removal of the chamber in an emergency difficult? Free-text follow-up was collected in the case of a ‘Yes’ response. Questionnaire responses and timing data were collected in a REDCap (Research Electronic Data Capture) database hosted at BC Children’s Hospital Research Institute (19, 20).
Statistical analysis
The sample size was calculated using the intubation times provided by Begley et al. when using their latest generation intubation box (5). Using 90% power and standard alpha=0.05 generated a sample size of 19, rounded up to 20 for paired analysis. Duration of the following intervals was calculated for each primary outcome in seconds: NPIC preparation time as TSTART to TNPIC; intubation time as TINT-START to TINT-FINISH; time to secure the ETT as TINT-FINISH to TSECURE; time to assess desaturation as TDESAT-START to TDESAT-DIAGNOSE (Figure 2). Time to intubation time to secure ETT, and time to assess desaturation are presented as median (interquartile range). Comparison between groups (with NPIC, without NPIC) was done using the Wilcoxon signed-rank test for paired data, with comparisons given as median difference with 95% confidence interval and p-value, and data were plotted using boxplots. Statistical analysis was performed using R v4.0.3 (R Foundation for Statistical Computing, Vienna, Austria). Aerosol data were analyzed using a linear mixed effects model to evaluate the effect of the NPIC on average particulate matter concentration throughout the complete trial and intermittently at 30 s intervals. The effect of the NPIC on average particulate matter concentration was estimated using a linear mixed effects model with random effects for trial number and participant ID and an interaction between NPIC presence and cubic regression splines (to allow for nonlinearity) for time from trial start. The overall difference in NPIC was calculated as a marginal mean difference between NPIC and no NPIC from this model with its corresponding 95% confidence interval.
Results
Participants and pre-study questionnaire
Twenty participants were recruited and completed the pre-study survey (Table 1). Only two (10%) participants reported previous experience with personal protective barriers for intubation. Six (30%) participants believed that a barrier would place a patient at increased risk during intubation, and one (5%) thought there would be no increased risk; similarly, six (30%) participants believed that a barrier would help to protect health care workers from aerosols during intubation, while one (5%) thought a barrier would not increase protection (Table 1).
Table 1: Participant demographics, previous experience with personal protective barriers for intubation and expectations expressed in pre-study survey.
|
Participant demographics |
Sex, female : male |
10 (50%) : 10 (50%) |
|
Height, cm |
170 (164-176) cm |
|
|
Use of eyeglasses |
10 (50%) |
|
|
Inadequately rested |
3 (15%) |
|
|
Role, staff : fellow |
18 (90%) : 2 (10%) |
|
|
Experience, <5y : 5-10y : >10y |
6 (30%): 3 (15%): 11 (55%) |
|
|
Experience and expectations |
Previous experience intubating with barrier |
2 (10%) |
|
Believed barrier may increase patient risk, |
6 (30%) : 13 (65%) : 1 (5%) |
|
|
yes : unsure : no |
||
|
Believed barrier may protect health care worker from aerosols, yes : unsure : no |
6 (30%) : 13 (65%) : 1 (5%) |
Data presented as n (%) for counts and median (interquartile range) for continuous measures.
Intubation trial data
Participants took a median (IQR) of 28.0 (27.0 – 32.8) s to intubate the mannikin with the NPIC vs 23.0 (21.0 – 27.2) s without the NPIC, prolonging intubation time by 7.5 s [95% CI 5.0 to 11.5; p<0.001] (Figure 3). Participants took 18.5 (17.0-29.0) s to secure the ETT with the NPIC vs 19.0 (14.0-23.0) s without the NPIC, prolonging time to securement by 5.0 s [95%CI 1.0 to 11.0; p=0.016]. In the simulated desaturation emergency, participants took 33.5 (30.0 to 36.0) s to assess the desaturation with the NPIC and 16.0 (15.0 – 17.0) s without the NPIC, increasing time to diagnosis by 17.0 s [95%CI 15.0 to 19.0; p < 0.001]. One participant required two attempts to intubate with the NPIC, whereas all intubation attempts without the NPIC were successful on the first pass. One participant experienced a breach in the seal of the NPIC sleeve, but no PPE breaches were recorded in either group.
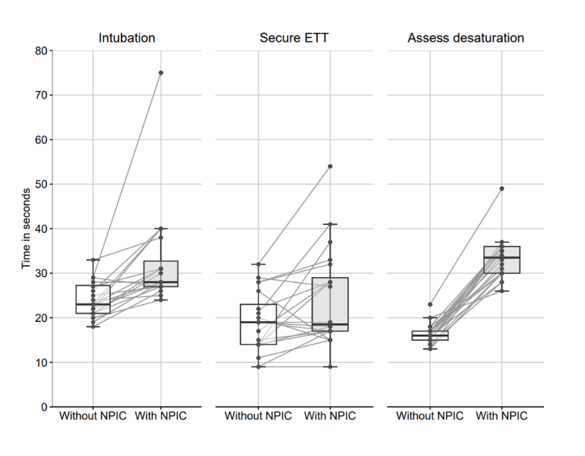
Figure 3: Box and whisker plot comparing time to completion of intubation, securement of endotracheal tube (ETT) and assessment of desaturation. Boxes encompass interquartile range with median marked in bold. Data points display individual time points, with lines linking data points from the same individual in different trials.
Post-study questionnaire
Eight (40%) participants considered intubation while using the NPIC more challenging, one (5%) considered preoxygenation with the NPIC more difficult, and four (20%) believed removal of the chamber in an emergency was difficult. Eight (40%) participants thought further improvements could be made to the arm positioning, four (20%) felt that the chamber significantly hindered visualization during the trial, and six (30%) considered gloving in the chamber was difficult. Free text comments discussed limitations to dexterity when using the NPIC, obstruction of the video screen of the laryngoscope, chamber ergonomics, concerns about NPIC removal in emergencies, and feasibility of use in awake pediatric patients or patients with challenging airways. Suggestions for ergonomic improvement included wider diameter arm holes to allow improved mobility and for arm holes to be further apart. Three (15%) participants also remarked that adjusting the arm holes relative to the airway in different-sized patients would be necessary, a feature of the NPIC design.
Aerosol data
The overall average particulate matter concentration measured near the participant during the trial was a mean (SD) of 26.6 (34.8) µg/m3 without the NPIC and 20.2 (33.4) µg/m3 with the NPIC, with an adjusted mean difference of -10.8 µg/m3 (95% CI -14.0 to -7.7, p<0.001). The average peak particulate matter concentration was mean (SD) 39.4 (46.3) µg/m3 at 180 seconds without the NPIC and 34.0 (52.3) µg/m3 at 90 seconds with the NPIC. The average particulate matter concentration, sampled every 30 s, was not different from the NPIC than without the NPIC during the first 60 s of the trial, but was lower at all points from 90 s onwards (Figure 4).
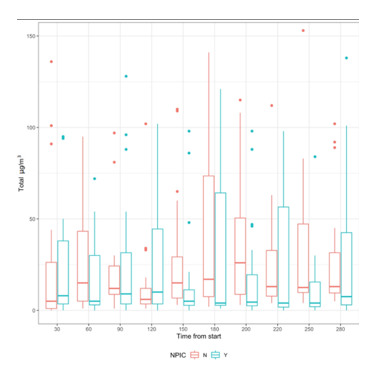
Figure 4: Comparison of the average particulate matter concentration measured near the participant at 30 s intervals between the cases with and without the negative pressure isolation chamber (NPIC). A linear mixed effects model indicated a significantly lower average particulate matter concentration with the NPIC than without at all time points from 90 s onwards. (The figure has been cropped at 150 µg/m3 for readability, which removed points at the 90 s, 220 s and 250 s timepoints).
Discussion
This study demonstrated that using the NPIC prolonged the time to conduct key airway management tasks, delaying intubation by 7.5 s, securing the ETT by 5 s, and emergency assessment of a desaturation event by 17.0 s. One participant required two attempts to intubate while using the NPIC, while all participants had first-pass intubation success without the NPIC. The NPIC was considered to have made intubation more difficult by eight (40%) participants, with concerns including obstructed video laryngoscope views and chamber ergonomics. However, NPIC use reduced the average particulate matter concentration at the position of the participant’s head by 10.8 µg/m3.
Comparison with previous studies
Though some studies have not found a significant change in intubation time with the addition of aerosol boxes (21-23), most studies to date have found statistically significant delays, in line with the results of this work. A systematic review found that aerosol boxes across 12 studies prolonged intubation times by a mean of 4.0 s (95% CI 2.4-5.6) (18), and other studies have found similar delays (8, 10, 14, 15). Idei et al. reported that using a video laryngoscope can offset intubation delays (2, 24), but that was not mirrored in this study. No studies have previously quantified the delay in accessing the patient in an emergency. A delay of 17 seconds in assessing a patient for desaturation is of concern and could potentially lead to patient harm. Increased intubation time and difficulty may be clinically significant, particularly for patients prone to rapid desaturation. However, studies using aerosol boxes in patients with a risk of difficult intubation (25) and children (26) found no increase in poor clinical outcomes or adverse events associated with intubation box use.
Improvements in usability and aerosol exposure
The NPIC design was intended to address issues with previous intubation boxes, including prolonged intubation time, increased intubation attempts, and PPE breaches (7-16) via the addition of adjustable arm port placement to improve patient access and plastic sleeves to seal the chamber and reduce PPE breaches. The modular design simplified storage and cleaning. Intubation delays and increased intubation attempts were not improved using the NPIC compared to other intubation boxes but did improve the occurrence of PPE breaches (8, 10, 12) as the only breach occurred in the sleeve of the NPIC, not in the participant’s PPE. Many previous box designs proved ineffective at protecting providers from aerosol exposure. Simpson et al. showed common box designs increased aerosol concentration near the provider, likely resulting from air forced from the arm holes (17). Hung et al. found reduced aerosol concentrations by the provider when boxes with high suction rates were used, but particles still escaped through unsealed armports (27). The NPIC was successful in addressing these issues by sealing the armports and adding extraction and inlet ports to enable the generation of negative pressure and direct airflow away from the provider, in line with the recommendations of other studies (9, 10, 25).
Ergonomic concerns
Impaired dexterity and limited range of motion in the NPIC were referenced in several post-study comments, a common concern in rigid barrier devices (7, 8, 16, 22). Lee-Archer et al. created an isolation chamber with large sidearm windows covered with plastic sheets, rather than typical armports (28) and found no significant delay in intubation. However, the box carried issues with protection from aerosols seen in other designs, indicating a tradeoff between increased patient access and provider protection. Other alternatives include aerosol “tents” and “bags” that enclose the patient with flexible materials, which may allow an increased range of motion for providers and have been shown not to delay intubation significantly (8).9 This style of barrier also holds promise in effectively reducing aerosols – Hung et al. found that an aerosol bag combined with wall suction was more effective at reducing aerosols than a rigid aerosol box (27). and warrants further investigation.
Conclusion
The NPIC delayed the time to intubation and diagnosis of an airway emergency by amounts that may be clinically significant in some patients. However, the NPIC also reduced total particulate matter measured near the provider’s head, which indicates it could reduce exposure to infectious aerosols during AGMPs. Therefore, using the NPIC may reduce the provider’s risk of infection but potentially increase the patient’s risk of an adverse outcome. The risk of brief delays in intubation may be offset by the benefits of administering high-flow oxygen and bag-mask ventilation in critically ill patients, initially advised against early in the pandemic. The use of an isolation chamber is not warranted currently. However, there will undoubtedly be future pandemics where the use of isolation chambers for airway management may again be considered, and this study adds valuable information for future design and testing.
Acknowledgements: This study was funded by the BC Children’s Hospital (BCCH) Foundation and a private donation from an anonymous “Creative Destructions” associate. The researchers would like to thank the BCCH pediatric anesthesiologists who participated in the study and the BCCH Simulation Centre for technical support. Dr. Andrew Morrison, Dr. Michael Barker and Dr. Louis Scheepers tested and provided technical feedback for early prototypes. The BC Institute of Technology engineering department constructed the prototype, Graphtech Designs, Jamie Martin and Tessa Martin, performed computer-aided design, and Patrick Rebstein with the Provincial Health Services Authority managed intellectual property. We would like to thank Krystal Cardinal for important work on data collection and early drafts of this study. The authors wish to thank Alex Zheng, Stefan Kojic, Fabio Magistris, and Gurmaan Gill for their support in operationalizing the study and contributing to its initial interpretation.
Funding: This study was funded by the BC Children’s Hospital (BCCH) Foundation and a private donation from an anonymous “Creative Destructions” associate. Dr Görges holds a Michael Smith Health Research BC Scholar salary award.
Competing Interests: The author(s) declare no competing interests.
Patient consent: Patients and/or the public were not involved in the design, or conduct, or reporting, or dissemination plans of this research.
Data Availability: Data can be made available upon request to Dr. Purdy.
Disclaimer: The developer of the NPIC, Dr. Robert Purdy, recused himself from participating in the study trials.
Disclosures: This study was funded by the BC Children’s Hospital (BCCH) Foundation and private donation from an anonymous “Creative Destructions” associate. Dr Görges holds a Michael Smith Health Research BC Scholar salary award.
Ethics Approval and Consent to Participate: Ethical approval was obtained from the University of British Columbia Children’s & Women’s Research Ethics Board (H20-01665; date of approval 2020-09-22; PI: R Purdy). Informed, written consent was obtained from all participants.
Consent to Publish
All authors have reviewed and approved the final manuscript and consent to its publication.
Authors contribution
Dr. Alberto Baldelli and Prof. Robert Purdy performed the experiments, wrote and revised the manuscripts. Dr. Robert Purdy. Andrew Poznikoff and Nicholas West supervised the process and provided insights. Jeffrey N. Bone, and Matthias Görges reviewed the manuscript.
Limitations
Our study's limitations include using a simulation manikin and aerosol model, which may not reflect in vivo patient use. While the indirect video laryngoscopy used in this study is recommended, other airway devices and techniques, including direct laryngoscopy, supraglottic airway devices, and fiberoptic intubation, were not tested and may be challenging with isolation chambers. While particle exposure was significantly reduced, the potential for exposure to viral aerosols remains. The preparation delay of the manuscript is of concern though we believe the information reported remains relevant.
References
- Fowler R.A, C.B. Guest, S.E. Lapinsky et al. Transmission of severe acute respiratory syndrome during intubation and mechanical ventilation. American journal of respiratory and critical care medicine 169 (2004): 1198-1202.
- Chan M.T, B.K. Chow, T. Lo et al., Exhaled air dispersion during bag-mask ventilation and sputum suctioning-Implications for infection control. Scientific Reports 8(2018): 198.
- Weissman D.N, M.A. de Perio, and L.J. Radonovich: COVID-19 and risks posed to personnel during endotracheal intubation. Jama 323 (2020): 2027-2028.
- Asadi S, N. Bouvier, A.S. Wexler et al. The coronavirus pandemic and aerosols: Does COVID-19 transmit via expiratory particles? pp. 635-638: Taylor & Francis 2020.
- Leal J, B. Farkas, L. Mastikhina et al. Risk of transmission of respiratory viruses during aerosol-generating medical procedures (AGMPs) revisited in the COVID-19 pandemic: a systematic review. Antimicrobial Resistance & Infection Control 11(2022): 102.
- Vaisman A, S. Hota. Aerosol-Generating Medical Procedures: Controversies in Definition, Risks, and Mitigation Strategies. In Infection Prevention: New Perspectives and Controversies, pp (2022): 387-394.
- Begley J, K. Lavery, C. Nickson, et al. The aerosol box for intubation in coronavirus disease 2019 patients: an in‐situ simulation crossover study. Anaesthesia 75 (2020): 1014-1021.
- Wong K.W, R.P.K. Lam, W.C. Sin, et al. Comparison of the efficiency and usability of aerosol box and intubation tent on intubation of a manikin using personal protective equipment: A randomized crossover study. The Journal of emergency medicine 61 (2021): 695-704.
- Lim Z.J, M.P. Reddy, D. Karalapillai, et al. Impact of an aerosol box on time to tracheal intubation: systematic review and meta-analysis. BJA: British Journal of Anaesthesia 126 (2020): e122.
- Li Y, Y. Fu, Y. Zhang et al. An overview of COVID-19 aerosol box for preventing droplet and aerosol contaminations in healthcare providers performing airway intubation. Drug Development and Industrial Pharmacy 47 (2021): 1693-1699.
- de Lima A, M.J. Chen, A. Abbas et al. Evaluating the use of an aerosol box during simulated intubations. Cureus 13 (2021).
- Price C.M, Ben-Yakov J. Choi A et al. Tawadrous: Barrier enclosure uses during aerosol-generating medical procedures: a scoping review. The American Journal of Emergency Medicine (2021) :209-218.
- Jones R.M, N. Andrus, T. Dominguezet al. Aerosol containment device design considerations and performance evaluation metrics. The American Journal of Emergency Medicine (2023):12-20.
- Christopher R.A, A. Lohanathan, D. Hazra et al. Performance of Aerosol Boxes for Endotracheal Intubation during the COVID-19 Pandemic with Systematic Review. Journal of Global Infectious Diseases 15(2023): 6-12.
- Harel D.S, Y. Lin, C.Y. Lo et al. Aerosol Box Use in Reducing Health Care Worker Contamination During Airway Procedures (AIRWAY) Study: Secondary Workload and Provider Outcomes in a Simulation-Based Trial. Pediatric Critical Care Medicine 1097.
- Fong S, E. Li, E. Violato et al. Gu: Impact of aerosol box on intubation during COVID-19: a simulation study of normal and difficult airways. Canadian Journal of Anaesthesia 68 (2020): 496.
- Simpson J, D. Wong, L. Verco, et al. Dzidowski, and P. Chan: Measurement of airborne particle exposure during simulated tracheal intubation using various proposed aerosol containment devices during the COVID‐19 pandemic. Anaesthesia 75 (2020): 1587-1595.
- Bennett J.A. The consolidated standards of reporting trials (CONSORT): Guidelines for reporting randomized trials. Nursing research 54 (2005): 128-132.
- Harris P.A, R. Taylor, R. Thielke et al. Research electronic data capture (REDCap) a metadata-driven methodology and workflow process for providing translational research informatics support. Journal of biomedical informatics 42 (2009): 377-381.
- Harris P.A, R. Taylor, B.L. Minor et al. The REDCap consortium: building an international community of software platform partners. Journal of biomedical informatics (2019): 103208.
- Querney J, J. Cubillos, Y. Ding, et al. Patient barrier acceptance during airway management among anesthesiologists: a simulation pilot study. Korean journal of anesthesiology 74 (2021): 254-261.
- Jen T.T, V. Gusti, C. Badh et al. The impact of a barrier enclosure on time to tracheal intubation: a randomized controlled trial. Canadian Journal of Anesthesia/Journal canadien d'anesthésie 68 (2021): 1358-1367.
- Kim H, J.E. Chang, D.K. Kim et al. Evaluation of the conventional and modified aerosol boxes during tracheal intubation in normal and difficult airways: a randomized, crossover, manikin simulation study. Journal of Clinical Monitoring and Computing 36 (2022): 1697-1702.
- Idei, M, T. Nomura, P. Jouvet et al. Video laryngoscope intubation with an aerosol barrier device: A randomized sequential crossover pilot study. Critical care explorations 2 (2020): e0234.
- Venketeswaran M.V, N. Srinivasaraghavan, K. Balakrishnan et al. Intubation outcomes using the aerosol box during the COVID-19 pandemic: A prospective, observational study. Indian Journal of Anaesthesia 65 (2021): 221-228.
- Trujillo A, F. Arango. Impact of aerosol box use on orotracheal intubaboxes usedmes in children. Paediatr Anaesth 31 (2021): 237-238.
- Hung T.Y, W.L. Chen, Y.C. Su et al. Comparing the effectiveness of negative-pressure barrier devices in providing air clearance to prevent aerosol transmission. Plos one 16(2021): e0250213.
- Lee‐Archer P, D. Boyd, T. Du et al. A comparison of anesthetic protective barriers for the management of COVID‐19 pediatric patients. Pediatric Anesthesia 31 (2021): 323-329.